

Transgender and gender-diverse individuals undergoing medical transition face distinct oral physiological alterations, surgical anatomical considerations, and systemic healthcare barriers that require informed, culturally humble dental management. Clinical avoidance and elevated rates of untreated periodontal disease and caries in this demographic frequently stem from previous negative experiences within healthcare settings, including administrative misgendering, invasive interpersonal questioning, and clinical refusal. Providing humanized dental care does not require political posturing; it requires clinical competence, respect for personal dignity, and rigorous knowledge of the physiological impacts of gender-affirming hormone therapy (GAHT) and facial gender-affirming surgery (FGAS). The dental team must understand the pharmacokinetic interactions of exogenous sex steroids on periodontal tissues, bone mineral density, and coagulation cascades, while cultivating an operatory environment that respects patient autonomy and privacy.
Exogenous hormone therapy exerts direct receptor-mediated biological effects on the oral mucosa, periodontium, and underlying alveolar bone. Feminizing hormone regimens typically combine exogenous estrogens (such as estradiol valerate or transdermal estradiol) with androgen receptor antagonists, including spironolactone, cyproterone acetate, or gonadotropin-releasing hormone (GnRH) analogs. Estrogen receptors (ER-alpha and ER-beta) located within gingival fibroblasts, osteoblasts, and endothelial cells modulate microvascular permeability and collagen turnover. High-dose systemic estrogen therapy increases gingival vascularity, accentuates cellular inflammatory responses to bacterial plaque, and occasionally provokes localized gingival erythema or hyperplastic responses reminiscent of pregnancy gingivitis, even in the presence of relatively low plaque scores. Conversely, androgen deprivation therapy, particularly prior to reaching steady-state estrogenic bone maintenance, or abrupt interruptions in hormone therapy, temporarily accelerates bone turnover, heightening vulnerability to alveolar bone resorption in patients with pre-existing chronic periodontitis.
Spironolactone introduces secondary clinical considerations due to its primary pharmacology as a potassium-sparing diuretic and aldosterone antagonist. Patients taking spironolactone frequently experience mild xerostomia, altered taste perception (dysgeusia), and orthostatic hypotension when rising quickly from a reclined dental chair. Salivary flow reduction diminishes oral clearing capacity and reduces salivary bicarbonate buffering, predisposing patients to cervical enamel demineralization and root surface decay. Dental professionals must monitor blood pressure at baseline and recommend non-pharmacological hydration strategies, neutral fluoride rinses, and sugar-free salivary substitutes containing xylitol. Furthermore, when prescribing non-steroidal anti-inflammatory drugs (NSAIDs) for post-operative analgesia, clinicians must exercise caution; combining high-dose NSAIDs with spironolactone increases the clinical risk of hyperkalemia and acute renal hypoperfusion.
Masculinizing hormone regimens centered on exogenous testosterone administration (intramuscular testosterone cypionate, enanthate, or transdermal gels) present alternative systemic and oral profiles. Androgen signaling stimulates sebaceous activity and can trigger moderate acne vulgaris extending to the perioral regions, which requires gentle handling during mouth retraction to prevent painful microtrauma. More importantly, exogenous testosterone elevates hematocrit and red blood cell mass via erythropoiesis stimulation, occasionally inducing secondary polycythemia. Elevated hematocrit increases blood viscosity and raises risks of thromboembolic events, especially if accompanied by cigarette smoking. Dental practitioners planning extensive oral surgical procedures should verify recent complete blood count parameters, ensuring hematocrit levels remain within normal reference ranges (below fifty percent) before elective surgery. While testosterone enhances bone mineral density and stimulates osteoblastic alkaline phosphatase activity, androgens also alter salivary cytokine profiles, promoting shifts in subgingival microbial composition toward higher anaerobic pathogenicity if periodontal maintenance is neglected.
Facial gender-affirming surgeries (FGAS) demand careful structural assessment by restorative dentists, orthodontists, and oral surgeons. Procedures such as mandibuloplasty, mandibular angle resection, genioplasty, and maxillary Le Fort osteotomies alter craniofacial skeletal proportions and modify soft tissue drape. When patients undergo mandibular angle contouring or chin narrowing, surgical osteotomies can inadvertently compromise the sensory pathways of the inferior alveolar nerve or mental nerve, resulting in temporary or permanent paresthesias of the lower lip and anterior labial gingiva. Dentists performing restorative procedures or administering mandibular block anesthesia must document pre-existing sensory deficits carefully before initiating treatment. Furthermore, surgical reduction of the chin or mandibular border modifies the insertion of the mentalis and digastric musculature, which alters lip posture, intraoral vestibular depth, and muscular seal during speech and mastication. When constructing removable partial dentures or designing anterior aesthetic restorations, clinicians must account for altered muscular vectors rather than applying standardized cis-normative proportions.
Orthodontic tooth movement and biomechanical tissue responses also demonstrate measurable interactions with gender-affirming hormone protocols. Both estrogen and testosterone influence bone turnover kinetics by modulating osteoclast apoptosis and stimulating osteoblast differentiation. In patients receiving high-dose feminizing estrogens, bone resorption rates can slow, potentially prolonging clear aligner or fixed bracket treatment intervals. Conversely, masculinizing testosterone therapy elevates bone turnover markers during initial therapy phases, which can temporarily accelerate tooth movement while increasing the metabolic demand on periodontal attachment apparatus. Orthodontists must collaborate closely with prescribing endocrinologists, monitoring radiographic root resorption and alveolar crestal levels with periodic bitewing and periapical imaging during active orthodontic mechanics.
Temporomandibular joint (TMJ) pathophysiology represents another significant area where endocrine status intersects with structural facial modifications. Female sex hormones, particularly estrogen and progesterone fluctuations, are well-documented modulators of TMJ disc ligament laxity, synovial fluid cytokine concentrations, and masticatory myofascial pain sensitivity. Transgender women initiating estrogen and anti-androgen therapy may experience a heightened susceptibility to myofascial pain dysfunction syndrome or internal disc derangements if pre-existing parafunctional bruxism or malocclusions are present. Concurrently, facial feminization surgery involving reduction mandibuloplasty alters the mechanical loading vectors across the temporomandibular condyle. Dentists must evaluate jaw range of motion, screen for joint clicking or crepitus, and fabricate customized nocturnal occlusal stabilization splints to protect both natural teeth and remodeled condylar structures from excessive nocturnal clenching forces.
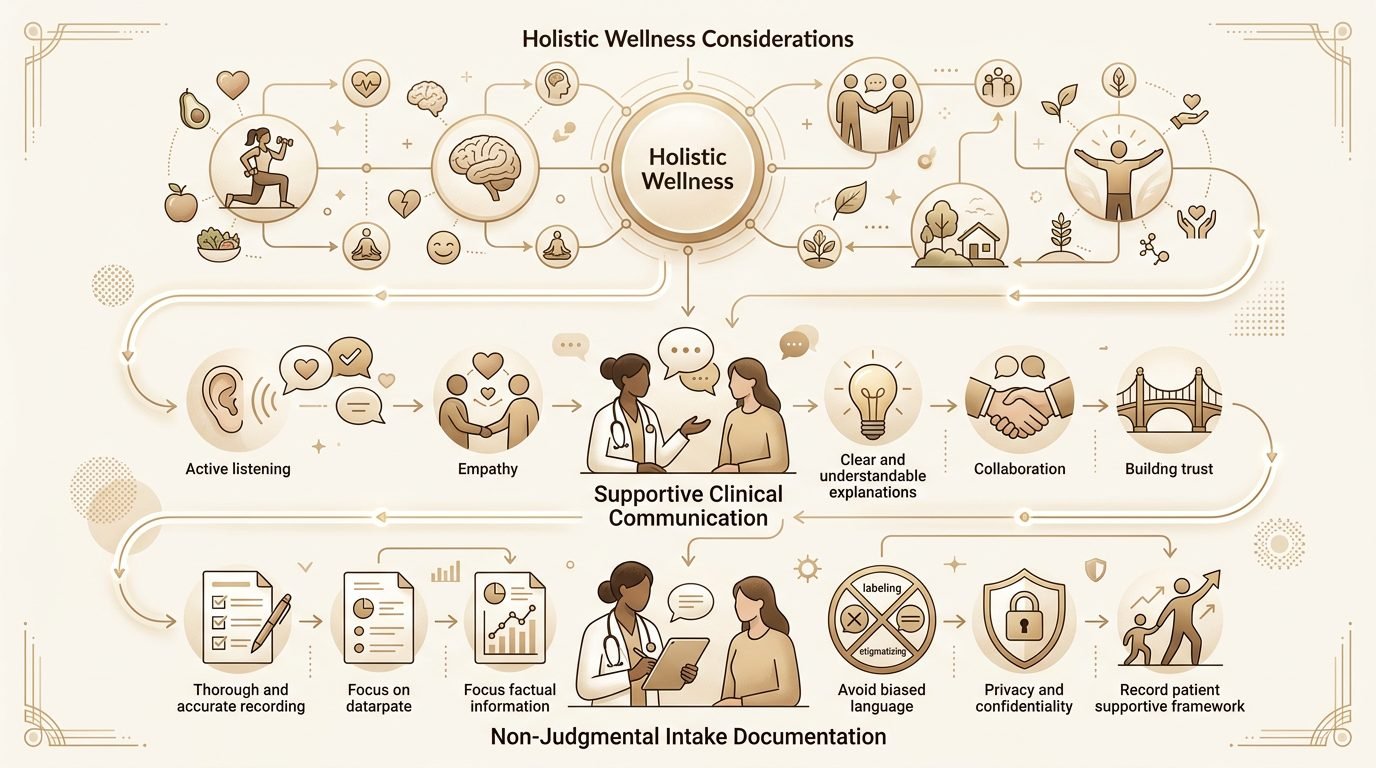
Affirming clinical communication constitutes an essential pillar of clinical safety and diagnostic accuracy. Patient registration protocols and electronic health records should incorporate inclusive intake fields that distinguish legal administrative names from affirmed names, and legal sex markers from affirmed gender pronouns. Clinical staff must be trained to use the patient’s affirmed name and correct pronouns consistently during verbal interactions, telephone scheduling, and chairside discussions. Repeatedly calling a patient by their legal deadname in an open waiting room constitutes a severe breach of privacy that induces intense psychological distress and promotes immediate healthcare avoidance. If a clinician inadvertently makes an error regarding a patient’s pronouns, the correct professional response is a brief, sincere correction followed by continuing the clinical conversation, avoiding prolonged emotional defensiveness that shifts psychological burden back onto the vulnerable individual.
Medical history documentation must remain strictly pertinent to clinical oral healthcare delivery. Inquiring about genital reconstruction surgery or private anatomical transition details when a patient seeks treatment for a localized molar pulpitis represents inappropriate voyeurism masquerading as medical history. Clinicians must maintain strict professional relevance, discussing only systemic medications, hormone dosages, surgical procedures that intersect craniofacial anatomy, and potential bleeding or thrombotic risk factors. Clear communication regarding procedural steps, transparent fee estimates, and unhurried verbal consent empowers patients who have historically experienced institutional coercion or discrimination.
Regarding professional standards, delivering dental care to transgender and gender-diverse patients exemplifies clinical excellence grounded in objective pharmacology and ethical patient-centered communication. By recognizing the mucosal and salivary consequences of hormone therapy, understanding the biomechanical sequelae of facial feminization and masculinization osteotomies, and enforcing affirming administrative workflows, dental teams eliminate long-standing healthcare disparities. This professional approach protects biological health, honors individual autonomy, and preserves dignity across every phase of the patient’s care experience.
Leave a Reply